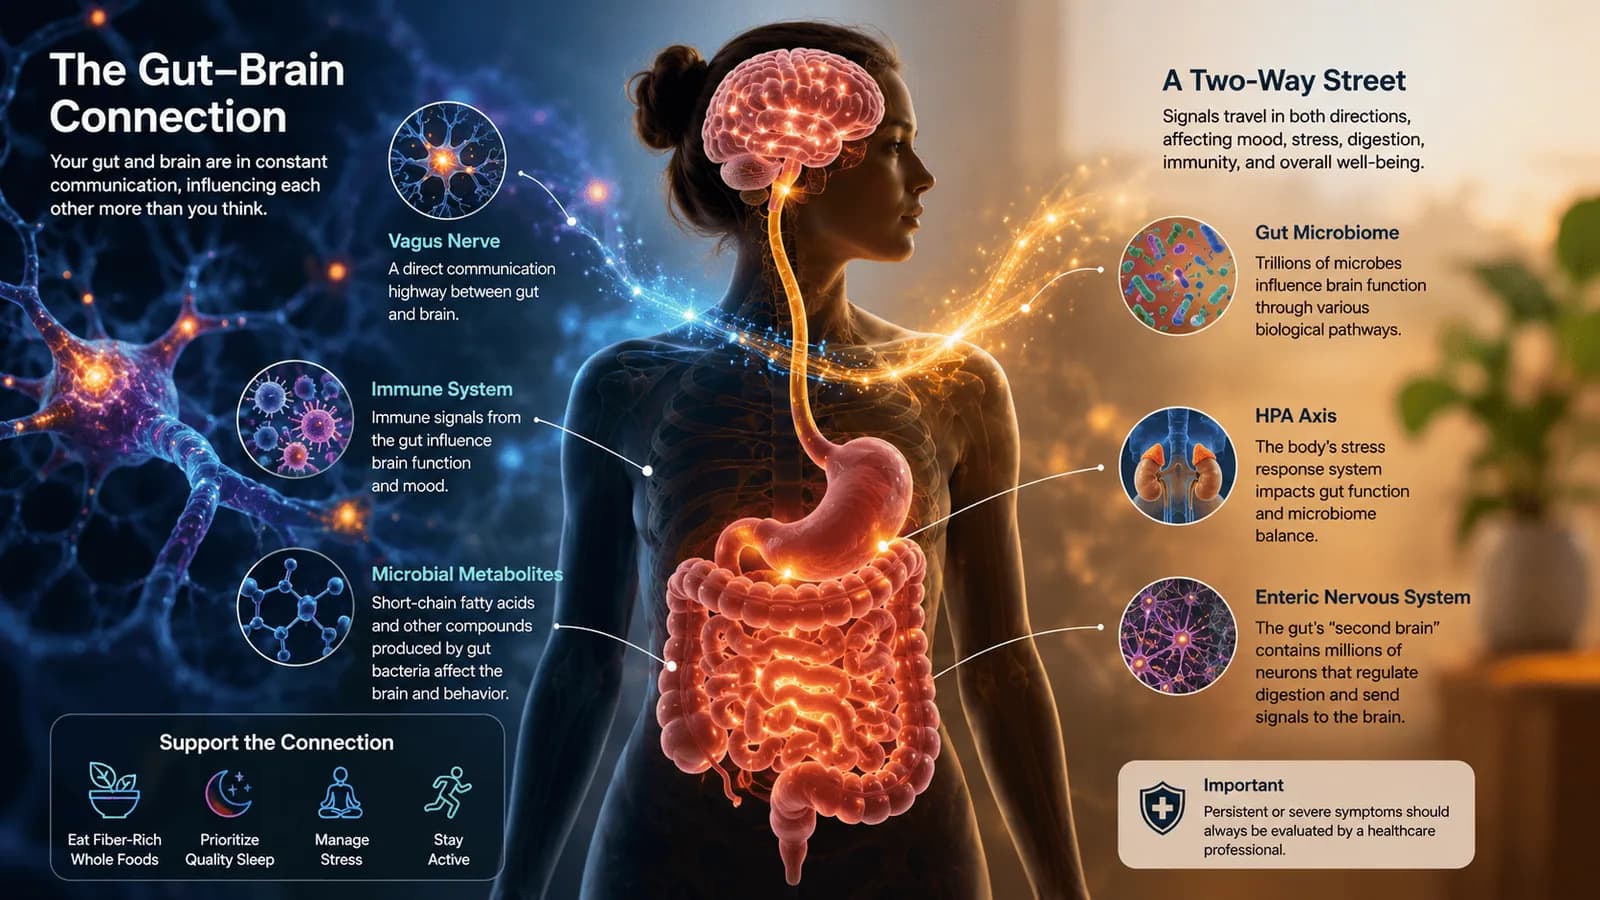
Quick Summary
For most healthy adults, a probiotic supplement is not necessary. The American Gastroenterological Association backs them in only three clinical situations, and suggests people taking them for IBS consider stopping. Benefits are strain-specific, and fermented foods have better trial support for everyday use.
For most healthy adults, the honest answer is no. That is not a fringe position: in 2020 the American Gastroenterological Association reviewed the trial evidence and recommended probiotics for only a short list of specific situations — and suggested that people taking them for common complaints such as IBS consider stopping.
That is close to the opposite of how probiotics are sold. The gap between the marketing and the evidence is the whole subject of this article, and it is worth understanding before you spend anything.
What a Probiotic Actually Is
A probiotic is a live microorganism that produces a health benefit when you take enough of it. The definition matters more than it sounds, because the benefit belongs to the specific strain — not to probiotics as a category, and not even to the species.
Strains are named in three parts: genus, species, and strain designation. Lacticaseibacillus rhamnosus GG has been studied in hundreds of trials. A different L. rhamnosus strain in a different capsule inherits none of that evidence. When a label says only “contains Lactobacillus,” it is telling you roughly as much as a bottle labeled “contains plants.”
The other number on the label is the CFU count — colony-forming units, meaning live organisms capable of reproducing. It gets printed in billions because billions sound impressive, but a higher count is not a better product. The doses that worked in trials range enormously by strain and by condition, and a strain studied at 10 billion CFU has no evidence behind it at 100 billion. Buying on CFU count is like choosing a medicine by the size of the tablet.
What matters more is when that count was measured. A product guaranteeing its CFU through the printed expiry date is making a commitment about what you will actually swallow. One declaring the count “at time of manufacture” is telling you what was true before shipping, warehousing, and the time it sat on a shelf — and live organisms die over that journey, faster if they were stored warm.
Probiotic, Prebiotic, Postbiotic
Three words get used interchangeably on packaging and mean quite different things. A probiotic is the live organism itself. A prebiotic is food for the organisms already living in you — typically a fiber your own enzymes cannot break down, such as inulin, resistant starch, or the fructans in onions, garlic and leeks, which ferment in the colon and feed resident bacteria. A synbiotic is the two sold together. A postbiotic is neither: it is the byproducts of fermentation, or deliberately inactivated organisms, with nothing live in the package at all.
The distinction has a practical edge. Prebiotics do not depend on anything surviving a journey through stomach acid, and they do not depend on colonization, because they feed the community you already have rather than trying to add to it. That makes their mechanism simpler and considerably harder to get wrong. It also makes them cheap: the fiber in a bowl of oats or a serving of beans does the same job as a prebiotic supplement, without the label.
It is worth knowing that prebiotic fiber is also the most common cause of the bloating people blame on probiotics. Fermentation produces gas by design. That is the mechanism working, not a sign of intolerance — though it is a reason to increase intake gradually rather than all at once.
What the Evidence Actually Supports
The AGA's guideline panel worked through 287 randomized controlled trials. Out of all of that, they found the evidence strong enough to recommend probiotics in three situations:
- Preventing C. difficile infection in adults and children taking antibiotics, using specific named strains
- Managing pouchitis, using one particular eight-strain combination
- Preventing necrotizing enterocolitis in preterm, low-birth-weight infants
Every one of those is a clinical situation with a supervising doctor. None of them is the reason most people buy probiotics.
Do They Actually Settle In?
There is a step most probiotic marketing skips: whether the organisms you swallow take up residence at all. A 2018 study went looking directly, and the answer turned out to be personal.
Rather than relying on stool samples, the researchers used endoscopy to sample the gut lining itself in healthy volunteers, before and during a four-week course of an 11-strain probiotic. The strains survived the trip — viability was not the problem. What varied was what happened next. Some people's guts were permissive, and the strains colonized the mucosa. Others were resistant, and the same product simply passed through, leaving the resident community essentially unchanged.
The most useful finding for anyone buying a product is a negative one. Stool samples could not tell the two groups apart. Strains showed up in the stool of people whose gut lining had rejected them entirely — because appearing in stool only proves something travelled the length of your intestine, not that it established anything. So the reassurance people reach for, that they can tell a probiotic is “working” because something is happening digestively, has no relationship to colonization.
Where colonization did occur, the effect on gut gene expression and community structure was transient and specific to the individual. The practical reading is not that probiotics never do anything. It is that whether a given product does anything in you is not predictable from the label, from the strain's trial record, or from how you feel — and nobody selling one can tell you in advance.
Why Most People Don't Need One
For irritable bowel syndrome, Crohn's disease, and ulcerative colitis, the AGA recommends probiotics only within a clinical trial — meaning the evidence is not yet good enough to say they help outside one. The panel went further and suggested patients taking them for these conditions consider stopping, on the grounds that the products cost money and the evidence is not sufficient to establish either benefit or absence of harm.
There is also a plausible mechanism for harm that rarely appears in marketing. A 2018 study found that taking probiotics after a course of antibiotics significantly delayed the recovery of the native gut microbiome compared with letting it repopulate on its own. The intuitive move — antibiotics wiped out my bacteria, so I should add bacteria back — may slow the thing it is meant to speed up.
It is also worth knowing what a label is permitted to claim. Supplements are not assessed for effectiveness before they go on sale the way medicines are, so a phrase like “supports digestive health” is marketing language rather than a regulator's finding. A product can carry that sentence without a single trial behind the particular formulation in the bottle, and without the manufacturer having to show that the strains inside are still alive by the time you swallow them.
Safety deserves more than the reassurance it usually gets. For healthy people, probiotics have a good record and serious harm is rare. The picture changes in specific groups, and the evidence here is not hypothetical. A study across five Finnish university hospitals identified 46 patients with Saccharomyces bloodstream infections between 2009 and 2018; at least 20 of them — 43 percent — were taking an S. boulardii probiotic at the time. Patients with fungemia had roughly fourteen times the odds of probiotic use compared with control patients, and those with gastrointestinal disease made up 59 percent of cases.
The European Medicines Agency reached a similar conclusion in 2017, judging that for critically ill or immunocompromised patients the risk of S. boulardii products outweighs the benefit. None of this makes probiotics dangerous for a healthy adult with an intact gut barrier. It does mean that “live bacteria and yeast” is a real category of intervention rather than a food-grade nicety, and that the people most likely to be handed one in hospital are sometimes the people least suited to it.
The Antibiotic Exception
Antibiotic-associated diarrhea is the one everyday case with real support. A 2012 meta-analysis of 82 trials found probiotics cut the risk by roughly 40 percent. The authors also flagged wide variation between studies and could not say which strain, dose, or patient it works best for — so this is a genuine effect with blurry edges, not a precise prescription.
Food Does More for Most People
A 2021 Stanford trial put healthy adults on either a high-fiber or a high-fermented-food diet for 17 weeks. The fermented-food group steadily gained microbiome diversity and showed decreases in inflammatory markers. The high-fiber group did not show the same effect over that period, and their response depended on the diversity they started with.
Fermented food is not a capsule with better branding. It delivers a wider mix of live cultures alongside the food matrix they arrived in, it costs less, and the trial evidence for everyday use in healthy people is stronger than for any supplement on the shelf.
| Fermented foods | Most supplements |
|---|---|
| Yogurt, kefir, kimchi, sauerkraut, miso | One or a few isolated strains |
| Diversity gains shown in a controlled trial | Benefits proven per strain, rarely for the product sold |
| Pennies per serving | Ongoing monthly cost |
| Doubles as food | Adds nothing nutritionally |
If you want to act on that, the useful move is variety rather than volume. Yogurt with live cultures, kefir, kimchi, sauerkraut, miso, tempeh and traditionally fermented pickles each carry different organisms, and rotating them covers more ground than a large daily serving of one. Two details separate a fermented food from something that merely tastes like one: it should be refrigerated, and it should not have been pasteurised after fermenting. Shelf-stable sauerkraut and most supermarket pickles are heat-treated or vinegar-brined, which is fine food and contains nothing live.
If You Take One, What to Look For
There are good reasons to take a probiotic — a doctor recommending one for a specific condition is the main one. If you are buying anyway, these are the things that separate a product with evidence behind it from one with a good label:
- The full strain designation is printed, not just the genus and species
- That exact strain has been trialled for your specific reason for taking it
- The CFU count is guaranteed through the expiry date, not merely at manufacture
- Storage instructions are stated and you can actually follow them
- The claims are specific and modest, rather than covering digestion, immunity, mood, and energy at once
Give it a defined trial rather than an open-ended subscription. Pick one reason you are taking it, one thing you would expect to change, and a window — four weeks is reasonable for most digestive complaints. If nothing you named has shifted by the end of it, that is your answer, and continuing out of vague hope is how a supplement becomes a standing order. Because response is individual in ways nobody can predict from the label, a product that did nothing for you is genuinely uninformative about the next one — which cuts both ways, and is an argument for spending less on the experiment, not more.
Frequently Asked Questions
Do I need a probiotic if I eat yogurt?
Probably not. Fermented foods such as yogurt and kefir deliver live cultures alongside food, and a 2021 Stanford trial found a high-fermented-food diet increased microbiome diversity and lowered inflammatory markers in healthy adults. For general gut health, food is the better-supported starting point.
Should I take a probiotic while on antibiotics?
It depends what for. Trial evidence supports specific strains for preventing antibiotic-associated diarrhea and C. difficile infection. But one study found probiotics taken after antibiotics delayed the native microbiome's recovery, so it is worth asking your prescriber rather than assuming.
How long does a probiotic take to work?
If a specific strain is going to help a specific condition, trials generally show effects within two to four weeks. If nothing has changed after a month, the strain is unlikely to be doing anything for you and continuing is mostly a cost.
Are more CFUs better in a probiotic?
No. The dose that matters is the one used in trials of that particular strain, which is often far below the highest counts advertised. A very high CFU number on the front of a package is a marketing signal more than a quality one.
Do probiotics help with IBS?
The American Gastroenterological Association recommends probiotics for IBS only within a clinical trial, because the evidence is not strong enough to support routine use. Their guidance suggests people taking them for IBS consider stopping.
References
- Su GL, Ko CW, Bercik P, Falck-Ytter Y, Sultan S, Weizman AV, Morgan RL. "AGA Clinical Practice Guidelines on the Role of Probiotics in the Management of Gastrointestinal Disorders." Gastroenterology, 2020;159(2):697-705.
- Hempel S, Newberry SJ, Maher AR, et al. "Probiotics for the Prevention and Treatment of Antibiotic-Associated Diarrhea: A Systematic Review and Meta-analysis." JAMA, 2012;307(18):1959-69.
- Suez J, et al. "Post-Antibiotic Gut Mucosal Microbiome Reconstitution Is Impaired by Probiotics and Improved by Autologous FMT." Cell, 2018;174(6):1406-1423.e16.
- Wastyk HC, et al. "Gut-microbiota-targeted diets modulate human immune status." Cell, 2021;184(16):4137-4153.e14.
- Zmora N, Zilberman-Schapira G, Suez J, et al. "Personalized Gut Mucosal Colonization Resistance to Empiric Probiotics Is Associated with Unique Host and Microbiome Features." Cell, 2018;174(6):1388-1405.e21.
- Rannikko J, et al. "Fungemia and Other Fungal Infections Associated with Use of Saccharomyces boulardii Probiotic Supplements." Emerging Infectious Diseases, 2021;27(8).